

Would you spend $100 to steal the exact case acceptance system we use (the actual scorecard, the actual presentation framework, the actual follow-up sequence) — so the revenue that's already in your practice finally shows up?
Earlier this year, I sat down with a practice owner who had a three-week wait for new patients.
The schedule was full.
The team was busy.
The owner was working five days a week and wondering why the bank account didn't reflect any of it.
When we pulled the numbers, the answer was uncomfortable.
The chair was full. But case acceptance was broken.
Patients were sitting in their chairs every day with diagnosed treatment they hadn't scheduled.
When patients did move forward, they were choosing the lowest-cost options — or no treatment at all.
The case mix that resulted was costing the practice far more than anyone realized.
The schedule was at capacity, but the procedures filling it weren't anywhere close to what the practice was capable of producing.
A full schedule is not the same as a productive one.
The difference almost always comes down to case acceptance — and what that case acceptance does to your case mix.
That gap, in this practice, was worth $310,000 a year.
When we rebuilt the system, that gap closed. The chair was still full. The production finally matched it.
But here's the part that stings more than the number: it wasn't just lost revenue. It's a practice running at full capacity — with a full team, a full schedule, and a full chair — and still not producing what it should. That's the invisible cost. And it compounds every single month.
The cost of poor case acceptance is invisible until you measure it.
Most practice owners track production. They track collections. They track new patients.
Almost nobody tracks what percentage of diagnosed treatment actually gets scheduled.
Or what that case acceptance rate is doing to their case mix — the blend of procedures that determines whether a practice runs at its potential or well below it.
Here's a number that will reframe how you see your own practice.
On average, practices schedule and complete about 25% of the treatment they diagnose.
If you're running a $1 million practice, that means roughly $3 million in diagnosed treatment never moved forward.
In your active patient base right now, millions of dollars in diagnosed, recommended care is sitting unscheduled.
When patients do say yes, poor case acceptance pushes them toward the least expensive options available.
Fillings instead of crowns.
Waiting instead of treating.
Not replacing missing teeth.
Opting out entirely.
That's not just lost production on individual cases — it's a case mix problem that compounds every single month.
We've seen hygiene departments running at 60% of their production potential — not because the hygienists aren't working hard, but because the system for presenting and scheduling care inside the hygiene appointment was never built.
And for practices participating in PPO networks, write-off rates can reach 50% of gross production — quietly erasing half of everything the team worked to produce.
A full chair with poor case acceptance is the most expensive problem in dentistry.
Because it's invisible, it's recurring, and the case mix it produces compounds in the wrong direction every single month.
Here's what I need you to know: a full schedule is a trap most practice owners don't see coming.
When you're trying to grow, a full schedule feels like success. You hit capacity. You stop worrying about new patients. You assume the revenue will follow.
It doesn't. Not automatically.
Because a full schedule just means you have the opportunity. It doesn't mean you have the system to make the most of it.
We spent years helping practices fill their schedules — and then watching owners arrive at full capacity and discover the revenue still wasn't where it should be.
The chair was full. Case acceptance was low. The case mix wasn't close to what the practice was capable of.
And the answer wasn't more patients. It was a better process for the ones already in their chairs.
Because the most expensive thing in a dental practice isn't an empty chair.
It's a full one where case acceptance is low and the case mix reflects it.
The backstory:
I've spent two decades helping dental practice owners build the systems that let them grow without working harder.
And for years, the growth conversation in dentistry was always the same: more new patients. Better marketing. Stronger recall. Fill the schedule.
I believed it.
I taught it.
I was wrong.
Not because new patients don't matter.
But because I was helping owners fill a chair where case acceptance was low and the case mix was suffering — and more patients just meant more revenue falling through the same gap.
The question most practice owners are actually asking isn't "how do I get more patients?"
It's "why isn't my full schedule producing what it should?"
Those are completely different problems.
And most owners spend years trying to solve the first one when the second is where all the leverage is.
I kept looking at the top of the funnel and ignoring what was happening in the chair.
Every time revenue was flat despite a full schedule, the advice was the same: market harder, see more patients, add another provider.
And it would work — for a while.
Then the schedule would fill again, case acceptance would decline, and the case mix would deteriorate.
The revenue gap would grow.
The schedule was a treadmill. We kept filling it. And the percentage of chair time that translated into high-value, scheduled, produced, and collected care barely moved — or even declined.
I didn't need a fuller schedule.
I needed to look at what was happening inside the one I already had.
So we rebuilt it.
We mapped every stage of the patient journey from the moment they sat down to the moment they either scheduled treatment or left without it.
We identified the three specific points where case acceptance was breaking down in practice after practice — and what that was doing to the case mix.
And we built a system that addresses all three.
And once you see it, you can't unsee it. 😮
So in this workshop, I want to give you the same system I built — compressed into 90 minutes, using your own numbers where available — so you can identify the gap and start fixing your case acceptance right now.
I still run my own practices. I've sat in the same chair you're sitting in.
Because if I was making this mistake (with everything I know, everything I teach, and my own practices to prove it) you're probably dealing with it too. 😉
Most practice growth advice is designed for practices that don't have enough patients.
More marketing.
Better SEO.
A stronger referral program.
That's not your problem.
You have patients. Your schedule is full. The problem isn't at the top of the funnel — it's what's happening once they're in the chair.
The process that turns a scheduled appointment into diagnosed treatment, and diagnosed treatment into a booked case — one that upgrades the case mix rather than degrading it — has never been built.
It runs on effort and instinct.
And effort and instinct don't scale.
Your team knows how to do dentistry.
That's not the same as having a system that produces the case acceptance and case mix your chair time should be generating.
95% of dental practice growth advice is designed to help you fill the schedule.
Not to build the system that improves case acceptance and upgrades what's being produced inside it — which, in most practices, is where most of the untapped revenue lives.
It's a completely different game.
Because a full chair with strong case acceptance and a productive case mix is a completely different business than a full chair without one.
I've now run this process with hundreds of dental practices.
The pattern is always the same.
Seven Pines Dental came to us with a full schedule and flat production. We rebuilt the case acceptance system from scratch and worked on upgrading their case mix. Over the next three years, they added over $1.6 million in production — not from new patients, but from improving what they were doing with the chair time they already had.
EMA Dental applied the hygiene case acceptance framework and generated over $1,000,000 in additional hygiene production in 12 months. Their newest hygienist produced $54,000 in a single month. The chair was already full. The case acceptance system wasn't built.
Dr. Henderson's practice doubled in five months. Not from a marketing campaign. From building the system that improved case acceptance and elevated the case mix across every provider.
A multi-location group was running at full capacity across three locations. We rebuilt the case acceptance process. Their acceptance rate moved from 38% to 61% in the following quarter — without adding a single new patient to the schedule. The case mix shifted dramatically. So did the revenue.
The pattern is always the same. The chair is full. Case acceptance is low. The case mix reflects it.
And once you build the system that fixes both, the revenue that was always there starts showing up.
I figured out exactly how to build this system.
And we'll work through it live, using your own numbers where available, in this workshop.
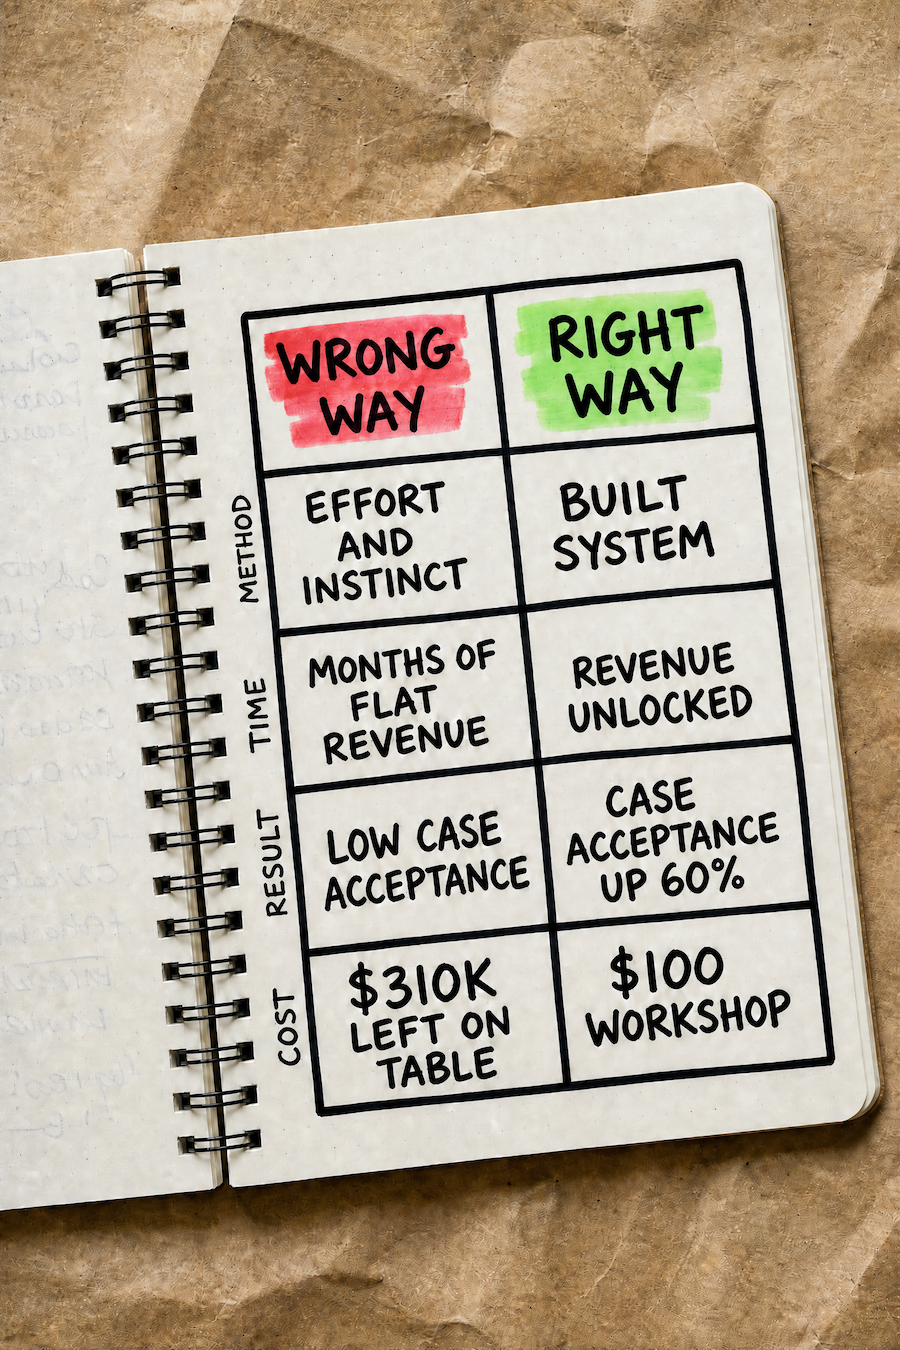
Here's how we'll fix your case acceptance:
We'll ignore everything you're "supposed" to do when production is flat — more marketing, more patients, another provider — and focus on what determines what a full chair produces: case acceptance, case mix, and revenue recovery. When those work together, you create production momentum.
First, you need to build a clear picture of what is happening in your practice before your team can improve it consistently. Case acceptance, case mix, and revenue recovery have to work together. Otherwise you're relying on whoever happens to be in the room, and effort fills every gap.
We call this part: BUILD IT.
Second, you need to use the model in your own practice. Not just hear the theory, but use your numbers to identify the gap, estimate the opportunity, and decide what needs attention first.
We call this part: USE IT.
Put them together, and that's The Full Chair™.
Here's how we'll do it:
First, we'll BUILD IT.
(This is the stage most practices have never built. It's the one that changes everything.)
Then, we'll USE IT.
Every side connected. Every number brought into focus. Every exercise designed to show you and your team what to address first.
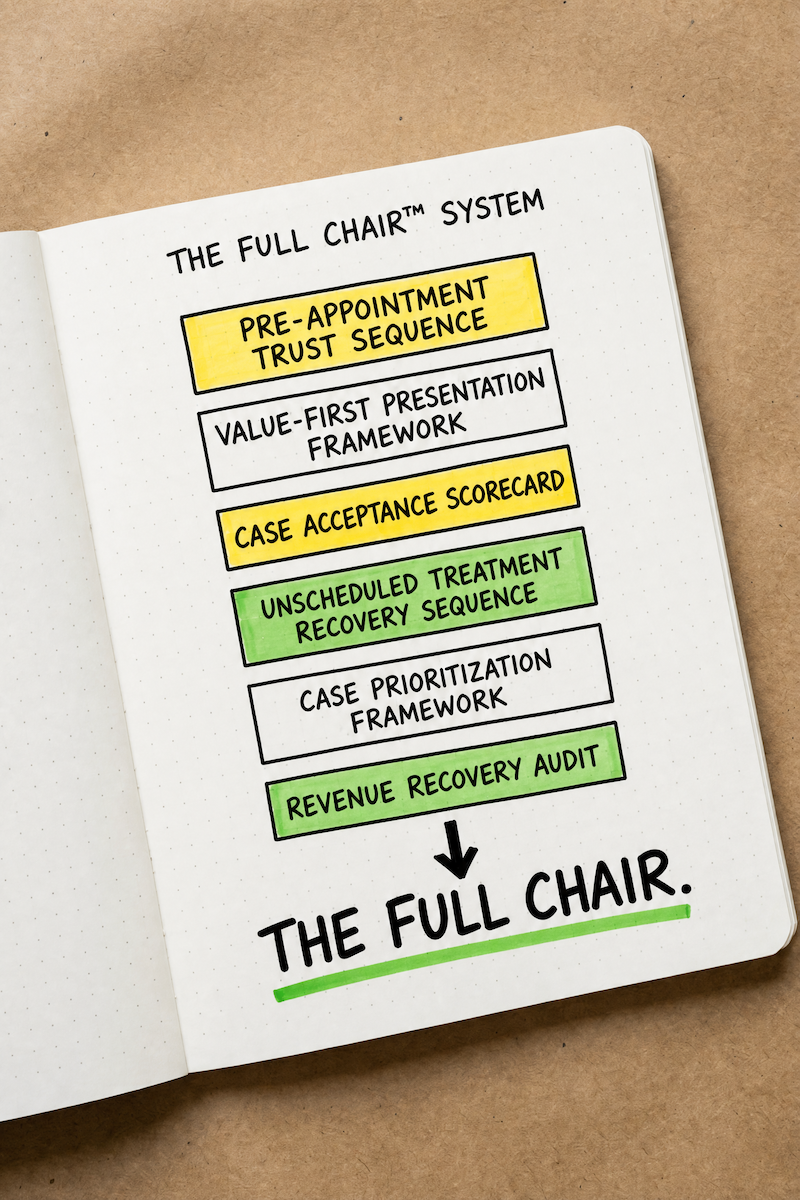
Throughout the workshop, you'll apply the model to your own practice — with both myself and Wendy in the room as you work.
You won't just understand how the system works.
You'll have identified your biggest gap, estimated the opportunity, and started mapping what to address first.
Logistics
This is a LIVE, hands-on working session.
Not a masterclass.
Not a presentation.
Not a "case acceptance tips" webinar.
Bring your current case acceptance rate if you know it. If you don't, come anyway — a rough estimate is enough, and not knowing is useful information. We'll show you where to begin.
Date: Tuesday, September 15, 2026
Los Angeles: 5:00pm Pacific
Dallas/Chicago: 7:00pm Central
New York: 8:00pm Eastern
Length: 90 Minutes
Presenters: Dr. John Meis & Wendy Briggs
Can’t make it live? You'll get the full recording and all resources by email after the workshop. But the live session — applying the model to your own practice with Dr. John and Wendy — is where the work happens. Show up if you can.
Your Investment:
$100 USD
Here's What We'll Cover
The Bonuses:
After the live workshop, we'll email you The Full Chair™ Toolkit:
The diagnostic tool that tells you exactly where your practice is losing production — in hygiene, treatment presentation, or follow-up — and what it's doing to your case mix. Use it after the workshop to confirm your priority and continue the work from the right starting point.
The exact language your hygienist uses to transition a patient from hygiene to treatment discussion in a way that feels natural, not salesy. The single highest-leverage script in the entire system.
A fill-in-the-blank framework for presenting any treatment case in a sequence that removes financial resistance before it forms. Same structure we use with every client.
The complete follow-up sequence for scheduling diagnosed-but-unscheduled treatment. Includes the exact messaging cadence, timing, and channel mix that recovers an average of $40,000–$80,000 within the first 90 days.
40+ real patient objections organized by type — financial, fear, time, and trust — with compliant, non-pressured responses that address the real concern underneath the stated one. Because "I need to think about it" is never really about thinking.
Watch and rewatch any time. We'll email your replay and toolkit after the live session so you can stay focused while Dr. John and Wendy are teaching.
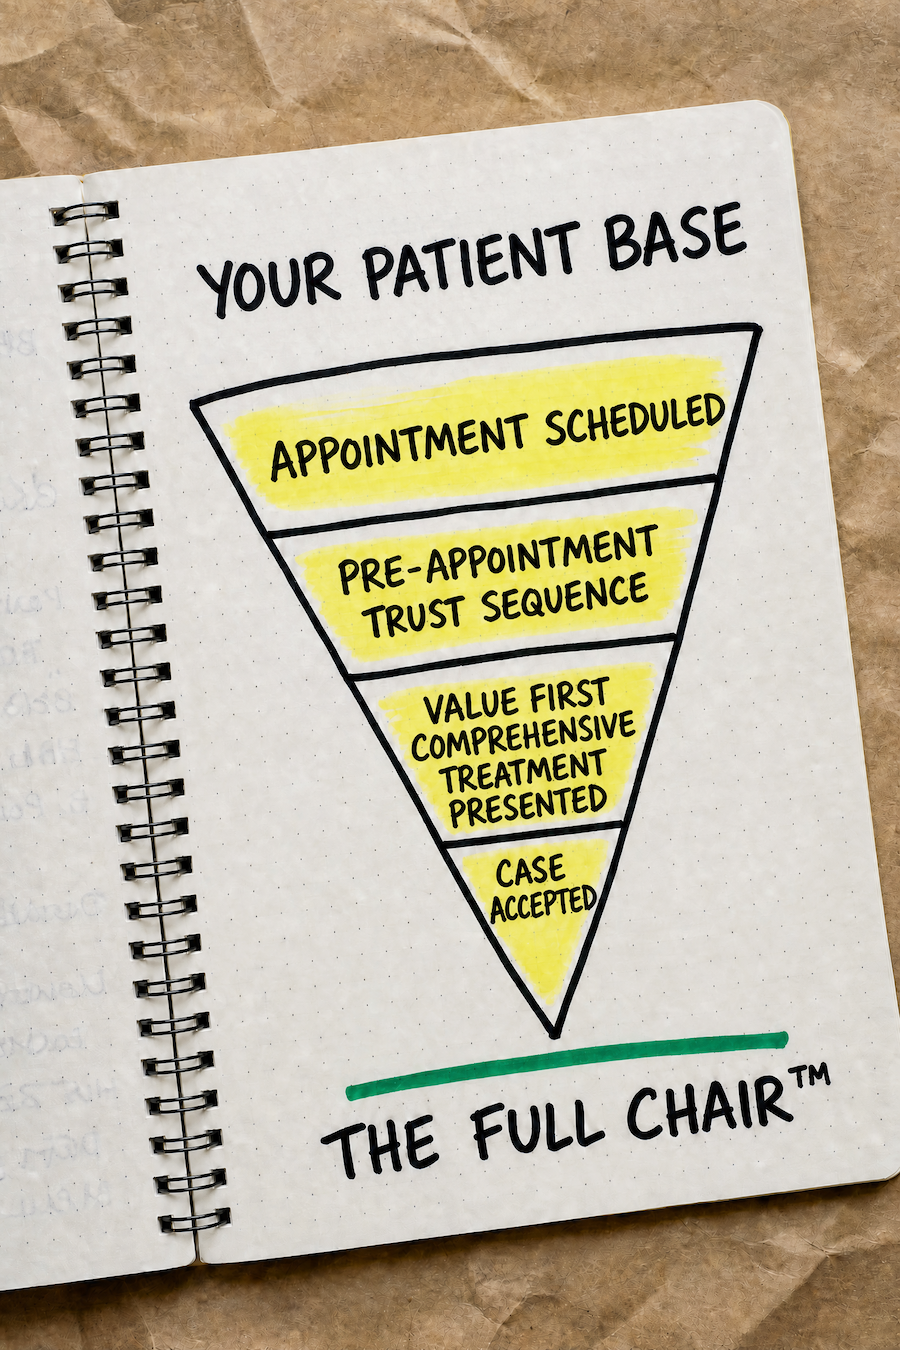
Don't come if...
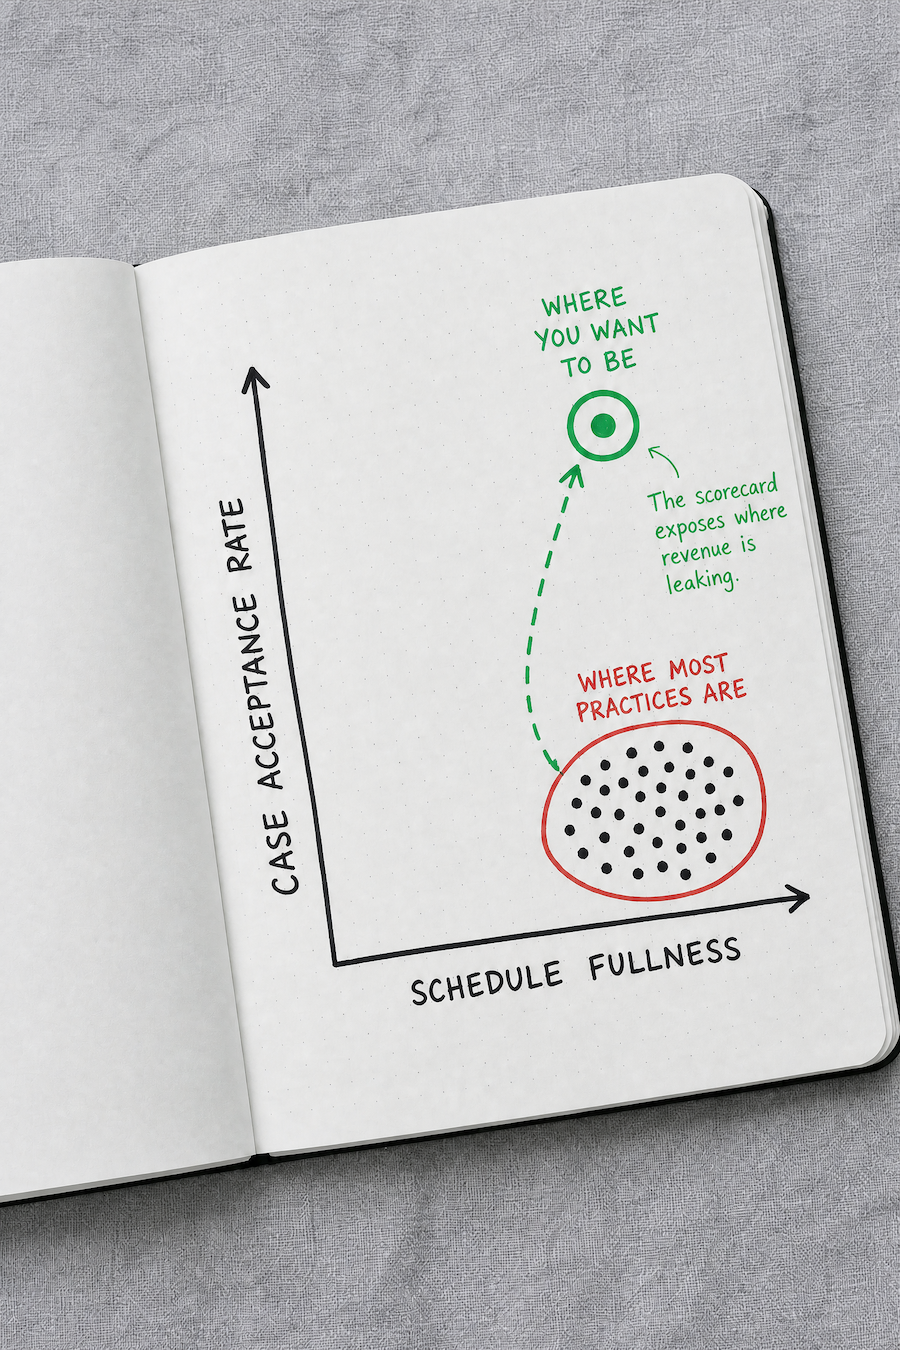
This is for practice owners who already know something is off. Owners who look at a full schedule and wonder why the revenue doesn't match the effort.
You've worked too hard to keep filling a chair that isn't producing the revenue and profit it should.
This workshop is the fastest way to build the system that fixes it.

Co-Founder, The Team Training Institute
Dr. Meis has spent two decades inside dental practices — not advising from a distance, but building the actual systems. He has personally coached hundreds of practices from stagnation to seven-figure growth, and has seen the case acceptance and case mix problem in every market, at every practice size.

Co-Founder, The Team Training Institute
Wendy Briggs is one of the most recognized names in dental hygiene production and team performance. She has trained thousands of dental professionals and is the architect of the hygiene case acceptance systems that have added millions in production to TTI client practices.